
OCD Treatment in New Jersey
Obsessive-Compulsive Disorder (OCD) is a mental health condition that causes unwanted, intrusive thoughts (obsessions) and repetitive behaviors (compulsions). These patterns can disrupt personal relationships, work, and daily life.
Without professional support, this cycle of obsessions and compulsions can become unmanageable. Capital Psychiatry Group provides trusted and evidence-based OCD treatment across New Jersey via in-person clinics and telepsychiatry. OCD is not a personality quirk or a love of tidiness; it is a treatable condition that changes how the brain responds to doubt and perceived danger. With the right therapy, many people see their compulsions shrink and their days open back up.


OCD Controls Your Day, Let’s Break the Cycle with CPG
About 2.3% of U.S. adults experience OCD at some point in their lives. It is a cycle of unwanted thoughts and exhausting ritual behaviors. You might be stuck checking the door, constantly washing your hands, or trying to silence your thoughts. The board-certified psychiatrists and licensed psychologists of Capital Psychiatry Group provide personalized, evidence-based treatment for OCD.
Whether you are struggling to take control of your thoughts or manage compulsions, our outpatient mental health clinics in New Jersey are always within reach with same-day appointments. Many people live with OCD for years before seeking help, often out of shame or fear about what their thoughts mean. Our clinicians understand these thoughts well, so you can describe even the most uncomfortable ones without fear of judgment.
Recognizing the Symptoms of OCD
What seems like a habit or routine may be your way, or your child’s way, of coping with OCD. Its symptoms don’t always look extreme; it can start with subtle signs. Recognizing the signs early is key to getting effective help. Most people with OCD know their thoughts or rituals are excessive, yet still feel unable to stop them. Symptoms point to OCD when they take up more than an hour a day or cause significant distress at home, school, or work.
Symptoms of OCD Obsessions
Obsessions are intrusive thoughts, urges, or mental images that create intense distress or anxiety. Common obsessive symptoms include:
- Fear of contamination by germs, dirt, or illness
- Intrusive and disturbing graphic images or thoughts
- Unwanted religious or blasphemous thoughts
- Extreme need for symmetry, precision, or exactness
- Unwanted thoughts of violent behavior toward yourself or others
Symptoms of OCD Compulsions
Compulsions are repetitive behaviors or mental acts performed to reduce the anxiety caused by OCD obsessions. Common symptoms of OCD compulsions include:
- Excessive hand washing, showering, or cleaning
- Repeated checking of locks, appliances, or switches
- Counting, tapping, or repeating words in a specific pattern
- Seeking reassurance from others over and over
- Mental rituals, such as praying, reviewing, or replacing a “bad” thought with a “good” one
Our OCD Treatment Process: What to Expect
Experienced providers at Capital Psychiatry Group evaluate, diagnose, and provide ongoing, personalized support. Your evaluation may include the Yale-Brown Obsessive Compulsive Scale (Y-BOCS), a standard tool that measures the severity of obsessions and compulsions. Your clinician will also screen for conditions that often occur alongside OCD, such as anxiety, depression, tic disorders, and skin picking or hair pulling.
- Our licensed psychiatrists/psychologists will ask questions about the obsessive thoughts and habits that affect your day.
- We will review your and your family’s mental health history.
- We follow DSM-5-TR criteria to evaluate and diagnose OCD.
- Together, we assess how OCD impacts your daily life.
- After diagnosis, our psychologist/psychiatrist will create a treatment plan.
- We offer therapy, counseling, and medication if needed.

Therapies and Counseling We Offer For OCD
The licensed psychologists at CPG offer a wide range of therapies and counseling, including Exposure and Response Prevention therapy, a specialized form of CBT considered the gold-standard therapy for obsessive-compulsive disorder. During ERP, you face feared thoughts or situations in small, planned steps while resisting the urge to perform compulsions, which teaches your brain that anxiety fades on its own. Exposures build gradually, and you and your therapist decide the pace together. Our therapy services include, but are not limited to:
Behavioral Therapy
Group Therapy (CBT-based)
Cognitive Behavioral Therapy (CBT)
Motivational Interviewing
Supportive Psychotherapy
Cognitive Therapy
Cognitive-Behavioral Family Therapy
Exposure and Response Prevention (ERP)
Mindfulness-Based Cognitive Therapy (MBCT)
Why Choose Us for OCD Treatment
The experienced psychiatrists and psychologists of CPG focus on creating a practical and customized treatment plan that helps you regain control of your daily functioning. When medication is part of the plan, our psychiatrists commonly prescribe SSRIs, which for OCD are often used at higher doses and given more time to work than for depression. Families can also join care and learn how to stop accommodating rituals at home, which supports recovery, especially for children. Patients across New Jersey trust Capital Psychiatry Group for OCD care because:
- All insurance plans are accepted
- Same-day appointments
- Board-certified psychiatrists
- In-person clinics across New Jersey
- HIPAA-compliant telepsychiatry
- Personalized treatment plans
- Exposure and Response Prevention (ERP)
- Walk-in appointments
- Therapy + Medication
The Cycle Feels Endless, CPG Helps You Press Pause
Whether you’re checking the door for the third time, washing your hands until they’re raw, or silencing “what if” thoughts that won’t quit, you’re not alone. At Capital Psychiatry Group, our providers help calm the noise at your pace, in your space. A frightening intrusive thought doesn’t mean you want to act on it. Recovery doesn’t mean having unwanted thoughts; it means they lose their grip on your day.
Areas Served Across New Jersey
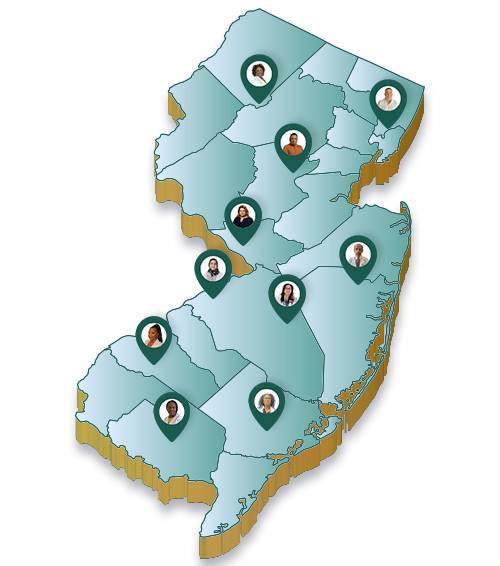
Capital Psychiatry Group’s in-person and online OCD services are available throughout New Jersey. Our outpatient mental health clinics deliver in-person treatment in Hamilton Township, Ewing Township, Newark, South Plainfield, Cinnaminson, and Delran. Together, these clinics bring ERP closer to families in North, Central, and South Jersey.
No matter where you live in NJ, with our telepsychiatry services, expert OCD care is just a click away. Online sessions are especially useful for ERP, since exposures can be practiced in the real places where compulsions happen, like your kitchen or front door.
There is no single cause of OCD. Research points to a combination of brain differences, genetics, and life experiences. Brain imaging studies show differences in circuits linking the front of the brain with deeper structures that filter thoughts and urges. That helps explain why intrusive thoughts feel so “sticky” and hard to dismiss.
Genetics play a role too. OCD is more common in people with a close relative who has it, especially when symptoms begin in childhood. Still, no single gene causes it, and many people with a family history never develop OCD.
Life events can trigger or worsen symptoms in people who are already vulnerable. These include major stress, pregnancy and childbirth, illness, and big transitions such as starting college or a new job. OCD is not caused by bad parenting, weak willpower, or something you did wrong. Understanding this often removes a layer of guilt that keeps people from seeking care.
OCD themes vary widely, and many go unrecognized because they don’t involve visible rituals. These subtypes aren’t separate diagnoses, but they describe common patterns.
“Pure O” describes OCD where compulsions are mostly mental, such as reviewing memories, analyzing feelings, or mentally checking. From the outside, nothing seems wrong.
Relationship OCD involves constant doubt about whether you truly love your partner or whether they’re “the one.”
Scrupulosity centers on fear of sinning, being immoral, or offending God, often leading to repeated confession or prayer.
“Just right” OCD drives actions to be repeated until they feel complete or balanced.
Health-focused OCD involves persistent fear of having or catching a serious illness, with repeated body checking or online symptom searching.
Every theme follows the same cycle of doubt, anxiety, and ritual, which is why ERP works across all of them. Naming your theme helps your therapist design exposures that target what you actually fear.
These can look alike, but they feel different from the inside. People with perfectionism or obsessive-compulsive personality disorder (OCPD) usually see their high standards and orderliness as correct and useful. Their traits fit their sense of self, even when they strain relationships.
OCD feels the opposite. The thoughts are unwanted, often feel foreign or disturbing, and the rituals bring only brief relief before the doubt returns. People with OCD typically wish they could stop.
Generalized anxiety disorder (GAD) involves ongoing worry about real-life concerns such as money, work, or health. It rarely comes with rituals designed to neutralize a specific fear. OCD worries tend to be more specific, less realistic, and tied to a ritual that “must” be done.
Some people have more than one of these conditions at once. A clear diagnosis matters because ERP, the core treatment for OCD, is structured very differently from standard therapy for perfectionism or general worry.
OCD is usually considered a long-term condition rather than one that is cured. Still, many people reach a point where symptoms are mild, infrequent, and no longer control their daily life. With effective treatment, some people go long stretches with very few symptoms.
The goal of treatment is not to eliminate every intrusive thought, since everyone has odd or unwanted thoughts at times. The goal is to change your response to them, so a passing thought no longer sets off hours of rituals, avoidance, or distress.
Symptoms can return during periods of stress, illness, or major life change. That’s why good treatment includes relapse prevention. You learn to spot early signs, such as a new ritual creeping in, and to apply ERP skills on your own. Some patients also schedule occasional booster sessions after finishing regular therapy, which helps keep progress steady over the long term.
Several medications are FDA-approved for OCD, including the SSRIs fluoxetine, fluvoxamine, sertraline, and paroxetine. Clomipramine, an older tricyclic antidepressant, is also approved and can be effective, though it tends to cause more side effects, so it’s often used after SSRIs have been tried.
If one SSRI doesn’t help enough, your psychiatrist may switch to another, since people respond differently to each. When partial improvement plateaus, adding a low dose of certain antipsychotic medications, such as aripiprazole or risperidone, can boost results for some patients.
For OCD that hasn’t responded to medication and therapy, deep transcranial magnetic stimulation (deep TMS) received FDA clearance for OCD in 2018. It uses magnetic fields to target brain circuits involved in OCD, without anesthesia. Medication works best alongside ERP rather than on its own. Your psychiatrist can coordinate referrals for advanced options when needed.
Ready to review your medication options? Call Capital Psychiatry Group at 609-323-5252 to book an evaluation with a board-certified psychiatrist.
Many people notice meaningful improvement within 12 to 20 weekly sessions, though timelines vary with severity, how many themes are involved, and how much practice happens between sessions. Some intensive programs compress treatment into several sessions a week for faster progress.
ERP starts with building an exposure hierarchy. This is a ranked list of situations or thoughts that trigger your OCD, from mildly uncomfortable to very difficult. You rate each one using a distress scale, often called SUDS (Subjective Units of Distress), so progress can be measured clearly.
Between sessions, you practice assigned exposures on your own, and this homework is where much of the change happens. Early sessions may feel harder before they feel easier, which is normal. As you move up the hierarchy, situations that once felt impossible gradually become manageable. Your therapist then shifts toward relapse prevention, so you can keep using these skills long after therapy ends. To start ERP with a licensed psychologist in person or online, call CPG at 609-323-5252.
Seeking reassurance is one of the most common OCD compulsions, and it’s easy to miss because it looks like an ordinary question. Asking “Are you sure the stove is off?” or “Do you still love me?” brings quick relief. That relief teaches the brain that the doubt was dangerous and needed answering, so the next doubt arrives stronger.
Over time, the reassurance stops working for as long. A single question turns into many, often asked to partners, parents, coworkers, or online searches.
For loved ones, the most helpful response is supportive but non-reassuring. Something like “I know this feels scary, and I believe you can handle the uncertainty” works better than answering the question again. This shift is hard for both sides and works best when planned with a therapist. Partners and family members can learn these responses in session, so everyone works toward the same goal instead of unintentionally feeding the cycle.
OCD often begins in childhood, but kids may hide rituals or lack the words to explain them. Parents commonly notice bedtime routines that take longer and longer, or homework that’s erased and rewritten until it looks “perfect.” Other signs include repeated questions, excessive handwashing, or distress when objects are moved.
Children may also show tantrums or meltdowns when a ritual is interrupted, which can be mistaken for defiance. Some avoid school, sleepovers, or certain foods because of contamination or harm fears they feel too embarrassed to describe.
In rare cases, OCD symptoms appear very suddenly, almost overnight, after an infection such as strep throat. This pattern is known as PANDAS or PANS and needs evaluation by both a pediatrician and a mental health specialist.
ERP is effective for children and is adapted to their age, often with parents taking part in sessions. Early treatment helps prevent OCD from affecting school performance and friendships. If you’re noticing these signs in your child, call 609-323-5252 to schedule a child OCD evaluation with Capital Psychiatry Group.
Unwanted thoughts about a baby being harmed, including thoughts of causing harm yourself, are surprisingly common after childbirth. When these thoughts are frequent, distressing, and lead to avoidance or rituals, they may point to perinatal OCD. This condition can start during pregnancy or after delivery.
Parents with perinatal OCD are horrified by these thoughts and often go to great lengths to prevent them. They may avoid bathing the baby, hide knives, or repeatedly check on the infant. These thoughts reflect fear, not intent. They are very different from postpartum psychosis, a rare emergency involving confusion, hallucinations, or a break from reality.
Many parents stay silent out of fear of being judged or having their child taken away. Clinicians who understand OCD recognize these thoughts for what they are. ERP is safe during pregnancy and breastfeeding, and your psychiatrist can review which medications are appropriate during this period. You don’t have to carry these thoughts alone. Call Capital Psychiatry Group at 609-323-5252 for confidential, judgment-free care.
Yes. OCD that substantially limits daily activities may qualify as a disability under the Americans with Disabilities Act (ADA) and the New Jersey Law Against Discrimination (LAD). These laws allow eligible employees to request reasonable accommodations without having to disclose every detail of their symptoms.
Common workplace accommodations include flexible scheduling for therapy appointments, modified deadlines during treatment, a quieter workspace, or written instructions that reduce the need for checking. Requests usually go through human resources and may require a letter from your treating provider.
Students have similar protections. College students can work with their school’s disability services office. K-12 students in New Jersey may qualify for a 504 plan or an IEP. Support can include extended test time, breaks, or adjusted assignments when rituals slow work down.
Your provider can document your diagnosis and recommend accommodations that support treatment goals. Accommodations should support ERP progress rather than make long-term avoidance easier.
Yes to both, and the first one matters more than people realize when comparing telehealth options. Some virtual platforms rotate you through whoever is available that day, which means repeating your history at every appointment. At Capital Psychiatry Group, you are matched with a specific clinician and stay with them.
That continuity is what allows someone to notice a medication that has stopped working, a seasonal pattern in your mood, or a change you have adapted to without registering it yourself. Switching between video and in-clinic appointments at any of our New Jersey locations is straightforward, and many CPG patients alternate depending on the week. Your record is identical either way, so nothing restarts and no history gets lost between formats.
It depends on what you are treating and which kind of care you are receiving, but there is a normal shape to it. You start with a longer initial evaluation, because your clinician is building the full picture. After that, follow-ups are shorter and more focused. Early on, visits tend to sit closer together so your clinician can see how you are responding, especially when a medication is new, and as things settle, they usually space out.
Therapy and medication care often run on different clocks. Therapy is frequently weekly or every other week while you are doing active work, whereas medication follow-ups may move to monthly or longer once you are stable. If you are doing both, your two schedules will not necessarily line up, and that is fine. None of this is fixed in advance. Your Capital Psychiatry Group clinician proposes a cadence and adjusts it with you, and if a week goes sideways between appointments, you are not expected to wait it out in silence.
Yes, and for some young patients the virtual format actually works better than a clinic visit does.
Teenagers in particular often speak more openly from their own room than across a desk from an unfamiliar adult, and the format removes the visible step of walking into a mental health office, which some adolescents resist strongly. For younger children, CPG sessions may be shorter or structured differently to hold attention, and parents are typically more involved in the process. A parent or guardian needs to arrange the appointment and be reachable during it.
The same confidentiality framework applies as for in-person adolescent care at our New Jersey clinics. Your teen's clinician sets out at the start what is shared with you and what stays in the session, with safety always the clear exception. Some situations still call for being in the room, particularly initial evaluations for complex presentations, and your CPG clinician will say honestly when that applies.
It happens, and there is a clear protocol rather than an awkward scramble. Your CPG clinician will have your phone number on file and will call you if the video fails. In most cases, the session simply continues by phone from where it stopped, so nothing is lost and the conversation carries on uninterrupted. If the connection cannot be restored at all, your appointment is rescheduled promptly and at no penalty to you. You will not be charged for a session that technology cut short, and you will not be pushed to the back of the queue.
A poor connection is often fixable in the moment by turning off your video and continuing with audio only, which uses far less bandwidth. Your clinician will suggest this if the picture starts breaking up before the call drops entirely.
Nearly everyone says this before their first Capital Psychiatry Group telehealth session, and nearly everyone reports afterward that the awkwardness faded within the first few minutes. The opening of a first session is largely practical. Your CPG clinician confirms who you are and where you are, explains how the session works, and asks what brought you in. It functions more like a structured conversation than a performance, and there is no expectation that you arrive with your thoughts organized or your situation neatly summarized.
Some patients find the screen actually makes difficult things easier to say, since being in your own space removes a layer of exposure that a clinical office can add. If you get partway through and decide the virtual format is not for you, say so. Moving to an in-clinic appointment at a New Jersey CPG location is simple, and nobody will treat it as a failed attempt. Trying it costs you very little and frequently changes the experience of care entirely.
If you are in immediate danger or having thoughts of harming yourself or someone else, do not wait for an appointment. Call or text 988 to reach the Suicide and Crisis Lifeline, available at any hour across New Jersey, or call 911, or go to your nearest emergency department. This is precisely why your CPG clinician confirms your physical location at the start of every session. If a safety concern arises mid-appointment, they need to be able to direct emergency services to where you actually are, and that information cannot be gathered usefully in the middle of a crisis.
Where risk is part of your clinical picture, your clinician will build a written safety plan with you early in treatment rather than waiting for something to happen. For urgent situations that are not emergencies, such as a medication reaction or a rapidly worsening week between scheduled appointments, call 609-323-5252, and the Capital Psychiatry Group team will arrange the fastest safe option available.
